
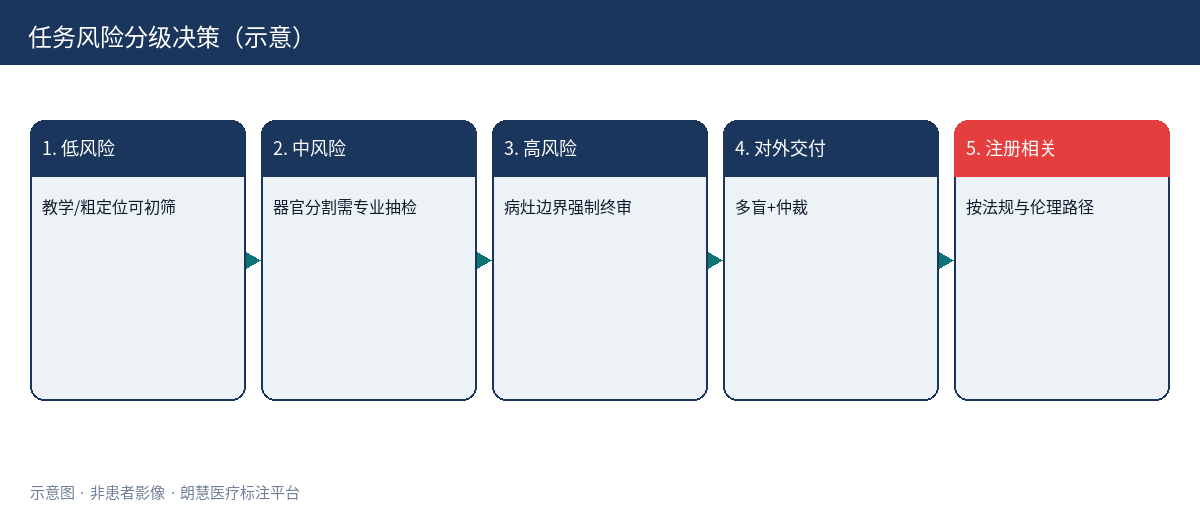
Bottom line: Crowdsourcing fits pre-screening and low-risk coarse tasks. Lesion boundaries, staging-related structures, external delivery, and regulatory-adjacent paths require professional medical annotation with expert final review and blind QC. Unit cost must not override defensibility.
2026 directions
Public practice emphasizes human-in-the-loop pre-labeling and multi-site collaboration without raw-pixel pooling. That supports “AI draft + professional gate,” not “drop the expert.”
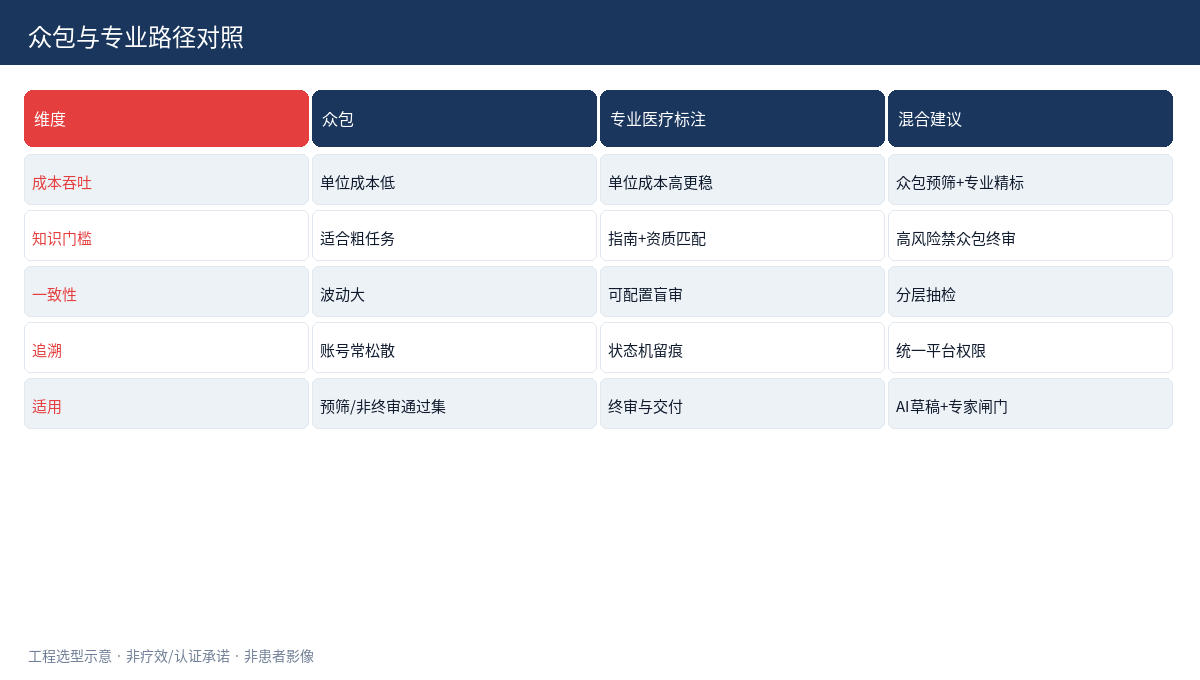
Comparison framework
| Dimension | Crowd | Professional | Hybrid |
|---|---|---|---|
| Cost/throughput | Lower unit cost | Higher, stabler | Crowd pre-screen + pro label |
| Knowledge | Coarse tasks | Guideline + role fit | No crowd final on high risk |
| Consistency | High variance | Blind review configurable | Stratified sampling |
| Provenance | Loose accounts | State-machine audit | One RBAC platform |
Prefer terms like final-accepted set or reference labels over clinical “reference-label set” wording that confuses diagnosis pathways.
Pitfalls
- Crowd roles that can one-click finalize → separate roles; lock templates.
- Pre-labels auto-ingested as final → draft state mandatory.
- Verbal QC only → demonstrate single-/multi-blind.
LangHui mapping
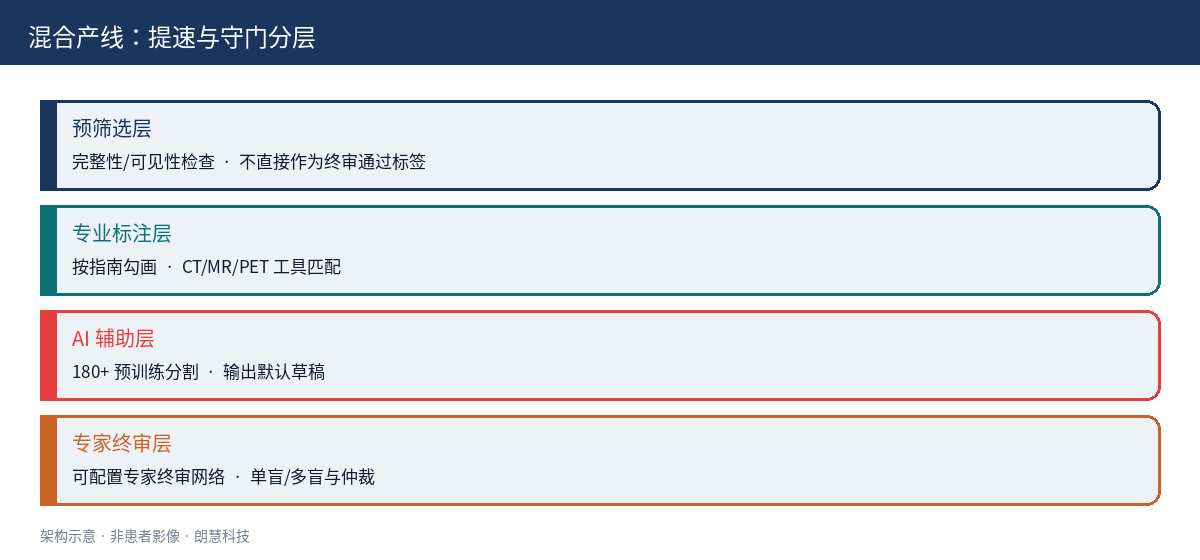
180+ segmentation drafts, single-/multi-blind, configurable expert final review, RBAC, on-prem, desensitization on upload, DICOM/nii/nrrd/Excel exports.
Account design for hybrid lines
Hybrid lines fail when the same account can both crowd-label and finalize. Split pre-screen, professional label, reviewer, and expert final-review roles. High-risk task templates should disable crowd finalization by default. For annotation vendors, do not market generic crowd capacity as a medical final-accepted set. For hospitals, policy red lines on off-site crowd labor outrank throughput experiments in a PoC.
Operational notes for procurement
Translate each checklist row into three columns in the RFP annex: requirement, evidence artifact, and non-conformity handling. Require the vendor to run the PoC on a timeline you control, with your roles (admin, labeler, reviewer, expert final reviewer) rather than a single superuser. Capture screenshots of fail-closed desensitization, a rejected case with reason codes, and an export opened in the receiving toolchain. Keep language free of absolute marketing adjectives and free of therapeutic promises.
For multi-site studies, document whether pixels, labels, or model updates move. If only labels or gradients move, say so explicitly. If pixels must never move, say that as a hard constraint and verify network controls during the PoC. Align contracts with PIPL/data-security themes applicable to your jurisdiction, and treat foreign frameworks such as HIPAA as principle references unless your counsel states otherwise.
LangHui Technology publishes product capabilities on langhuiai.com without fabricating traffic metrics or unverifiable accuracy numbers. Use those public facts as the ceiling for marketing claims in your own internal decks. When in doubt, demote a claim to “engineering practice direction” and ask for a staged proof.
Finally, keep the earlier Chinese pillar articles under medical-annotation-seo-2026 as complementary reading for YY/T educational mapping and dataset QC narratives. This 2026 matrix focuses on selection intent queries and bilingual discoverability with hreflang between zh-CN and en.
Operational notes for procurement
Translate each checklist row into three columns in the RFP annex: requirement, evidence artifact, and non-conformity handling. Require the vendor to run the PoC on a timeline you control, with your roles (admin, labeler, reviewer, expert final reviewer) rather than a single superuser. Capture screenshots of fail-closed desensitization, a rejected case with reason codes, and an export opened in the receiving toolchain. Keep language free of absolute marketing adjectives and free of therapeutic promises.
For multi-site studies, document whether pixels, labels, or model updates move. If only labels or gradients move, say so explicitly. If pixels must never move, say that as a hard constraint and verify network controls during the PoC. Align contracts with PIPL/data-security themes applicable to your jurisdiction, and treat foreign frameworks such as HIPAA as principle references unless your counsel states otherwise.
LangHui Technology publishes product capabilities on langhuiai.com without fabricating traffic metrics or unverifiable accuracy numbers. Use those public facts as the ceiling for marketing claims in your own internal decks. When in doubt, demote a claim to “engineering practice direction” and ask for a staged proof.
Finally, keep the earlier Chinese pillar articles under medical-annotation-seo-2026 as complementary reading for YY/T educational mapping and dataset QC narratives. This 2026 matrix focuses on selection intent queries and bilingual discoverability with hreflang between zh-CN and en.
Operational notes for procurement
Translate each checklist row into three columns in the RFP annex: requirement, evidence artifact, and non-conformity handling. Require the vendor to run the PoC on a timeline you control, with your roles (admin, labeler, reviewer, expert final reviewer) rather than a single superuser. Capture screenshots of fail-closed desensitization, a rejected case with reason codes, and an export opened in the receiving toolchain. Keep language free of absolute marketing adjectives and free of therapeutic promises.
For multi-site studies, document whether pixels, labels, or model updates move. If only labels or gradients move, say so explicitly. If pixels must never move, say that as a hard constraint and verify network controls during the PoC. Align contracts with PIPL/data-security themes applicable to your jurisdiction, and treat foreign frameworks such as HIPAA as principle references unless your counsel states otherwise.
LangHui Technology publishes product capabilities on langhuiai.com without fabricating traffic metrics or unverifiable accuracy numbers. Use those public facts as the ceiling for marketing claims in your own internal decks. When in doubt, demote a claim to “engineering practice direction” and ask for a staged proof.
Finally, keep the earlier Chinese pillar articles under medical-annotation-seo-2026 as complementary reading for YY/T educational mapping and dataset QC narratives. This 2026 matrix focuses on selection intent queries and bilingual discoverability with hreflang between zh-CN and en.
Operational notes for procurement
Translate each checklist row into three columns in the RFP annex: requirement, evidence artifact, and non-conformity handling. Require the vendor to run the PoC on a timeline you control, with your roles (admin, labeler, reviewer, expert final reviewer) rather than a single superuser. Capture screenshots of fail-closed desensitization, a rejected case with reason codes, and an export opened in the receiving toolchain. Keep language free of absolute marketing adjectives and free of therapeutic promises.
For multi-site studies, document whether pixels, labels, or model updates move. If only labels or gradients move, say so explicitly. If pixels must never move, say that as a hard constraint and verify network controls during the PoC. Align contracts with PIPL/data-security themes applicable to your jurisdiction, and treat foreign frameworks such as HIPAA as principle references unless your counsel states otherwise.
LangHui Technology publishes product capabilities on langhuiai.com without fabricating traffic metrics or unverifiable accuracy numbers. Use those public facts as the ceiling for marketing claims in your own internal decks. When in doubt, demote a claim to “engineering practice direction” and ask for a staged proof.
Finally, keep the earlier Chinese pillar articles under medical-annotation-seo-2026 as complementary reading for YY/T educational mapping and dataset QC narratives. This 2026 matrix focuses on selection intent queries and bilingual discoverability with hreflang between zh-CN and en.
Operational notes for procurement
Translate each checklist row into three columns in the RFP annex: requirement, evidence artifact, and non-conformity handling. Require the vendor to run the PoC on a timeline you control, with your roles (admin, labeler, reviewer, expert final reviewer) rather than a single superuser. Capture screenshots of fail-closed desensitization, a rejected case with reason codes, and an export opened in the receiving toolchain. Keep language free of absolute marketing adjectives and free of therapeutic promises.
For multi-site studies, document whether pixels, labels, or model updates move. If only labels or gradients move, say so explicitly. If pixels must never move, say that as a hard constraint and verify network controls during the PoC. Align contracts with PIPL/data-security themes applicable to your jurisdiction, and treat foreign frameworks such as HIPAA as principle references unless your counsel states otherwise.
LangHui Technology publishes product capabilities on langhuiai.com without fabricating traffic metrics or unverifiable accuracy numbers. Use those public facts as the ceiling for marketing claims in your own internal decks. When in doubt, demote a claim to “engineering practice direction” and ask for a staged proof.
Finally, keep the earlier Chinese pillar articles under medical-annotation-seo-2026 as complementary reading for YY/T educational mapping and dataset QC narratives. This 2026 matrix focuses on selection intent queries and bilingual discoverability with hreflang between zh-CN and en.
From gap analysis to contract annex
After reading the matrix, spend five working days on an internal gap analysis. Day one: IT sketches the network boundary and residency status. Day two: the research office lists modalities, approximate cohort size ranges, and whether guidelines are frozen. Day three: QC owners define when single-blind or multi-blind triggers. Day four: counsel or ethics staff verify authorization scope and retention. Day five: consolidate must / nice / never columns, then book a LangHui Medical Annotation Platform demo or another shortlist candidate against the same sheet.
Contract annexes should include topology and egress lists, desensitization policies, RBAC matrices, state transitions, export formats and version fields, PoC pass criteria, operations duties for patching and account revocation, and the path to expert final review. Prefer process verbs—“fail closed on ingest”, “pre-labels remain drafts”—over unverifiable adjectives.
Foundation-model buyers should emphasize provenance: who labeled and reviewed under which guideline version, how sampling metrics are defined, how exclusion lists are maintained, and how batch IDs map to training runs. Hospital buyers should emphasize on-site residency, desensitization on upload, exportable audits, and ethics packets. Do not copy throughput marketing from dataset vendors into hospital projects unchanged.
QC calendar and stratified sampling
Blind-review features do not replace a sampling calendar. Tier by risk: integrity checks for low risk; stratified samples for medium risk; higher review rates plus configurable expert final review for high risk. Feed top error types back into guideline edits and dictionary freezes. Define Dice/Kappa-style metrics yourselves; do not accept fabricated public accuracy or customer-count claims. LangHui’s public materials intentionally stay within verifiable tooling and deployment facts.
Training and trial rounds
Run at least two trial rounds before production: boundary calibration, then blind review with dispute taxonomy. Use authorized site data that includes artifacts and anatomical variants. Archive training records, guideline versions, and pass criteria. External collaborators get separate roles and timely offboarding. Any remote support egress on private installs must be approved and time-boxed—these details decide whether “data never leaves” survives an audit.
Reading order: the matrix article closest to your intent, then the product dual-path matrices, then optional earlier Chinese pillars under medical-annotation-seo-2026. English pages live under /en/news/medical-annotation-matrix-2026/ with hreflang both ways. Compliance: no absolute ad claims; no therapeutic substitution language; HIPAA principle-aligned only; YY/T educational only; vendor credentials never replace customer duties under privacy and data-security regimes applicable to you.
From gap analysis to contract annex
After reading the matrix, spend five working days on an internal gap analysis. Day one: IT sketches the network boundary and residency status. Day two: the research office lists modalities, approximate cohort size ranges, and whether guidelines are frozen. Day three: QC owners define when single-blind or multi-blind triggers. Day four: counsel or ethics staff verify authorization scope and retention. Day five: consolidate must / nice / never columns, then book a LangHui Medical Annotation Platform demo or another shortlist candidate against the same sheet.
Contract annexes should include topology and egress lists, desensitization policies, RBAC matrices, state transitions, export formats and version fields, PoC pass criteria, operations duties for patching and account revocation, and the path to expert final review. Prefer process verbs—“fail closed on ingest”, “pre-labels remain drafts”—over unverifiable adjectives.
Foundation-model buyers should emphasize provenance: who labeled and reviewed under which guideline version, how sampling metrics are defined, how exclusion lists are maintained, and how batch IDs map to training runs. Hospital buyers should emphasize on-site residency, desensitization on upload, exportable audits, and ethics packets. Do not copy throughput marketing from dataset vendors into hospital projects unchanged.
QC calendar and stratified sampling
Blind-review features do not replace a sampling calendar. Tier by risk: integrity checks for low risk; stratified samples for medium risk; higher review rates plus configurable expert final review for high risk. Feed top error types back into guideline edits and dictionary freezes. Define Dice/Kappa-style metrics yourselves; do not accept fabricated public accuracy or customer-count claims. LangHui’s public materials intentionally stay within verifiable tooling and deployment facts.
Training and trial rounds
Run at least two trial rounds before production: boundary calibration, then blind review with dispute taxonomy. Use authorized site data that includes artifacts and anatomical variants. Archive training records, guideline versions, and pass criteria. External collaborators get separate roles and timely offboarding. Any remote support egress on private installs must be approved and time-boxed—these details decide whether “data never leaves” survives an audit.
Reading order: the matrix article closest to your intent, then the product dual-path matrices, then optional earlier Chinese pillars under medical-annotation-seo-2026. English pages live under /en/news/medical-annotation-matrix-2026/ with hreflang both ways. Compliance: no absolute ad claims; no therapeutic substitution language; HIPAA principle-aligned only; YY/T educational only; vendor credentials never replace customer duties under privacy and data-security regimes applicable to you.
LangHui Medical Annotation Platform — Capability Map
Public product capabilities mapped to this article (educational reference; not a certification or clinical claim):
- Models & modalities: 180+ pretrained segmentation models; CT / MR / PET; MPR 3D verification.
- QC & review: single-blind / multi-blind review; status workflow; configurable expert final-review network.
- Security & deployment: desensitization on upload; role isolation; on-premises so data stays in the customer environment. Vendor security credentials do not replace the customer's classified-protection / privacy / ethics duties.
- Export: DICOM / nii.gz / nrrd / Excel packages with version freeze for reproducibility.
Product: Annotation Platform · About
FAQ
When is crowd finalization forbidden?
Lesion boundaries, staging-related structures, external delivery, regulatory-adjacent paths.
What can crowd still do?
Pre-screen and low-risk coarse checks with sampling; not final-accepted sets by default.
Is AI pre-label 'professional'?
No—assistance only; professionalism is guideline execution plus gates.
How to stop mis-finalization?
RBAC separation; lock high-risk templates.
Hybrid line pattern?
Pre-screen → pro label → AI draft → expert final review on one auditable platform.
LangHui support?
180+ drafts, blind review, configurable expert final review, on-prem, desensitization.
Book a demo: selection, QC, and on-prem in one platform
LangHui Medical Annotation Platform: 180+ segmentation models, CT/MR/PET, MPR, single-/multi-blind review, desensitization on upload, on-premises.
View platform Contact / demo